





Can an inherited DNA change rival a lifetime of heavy smoking? Scientists have discovered that a rare genetic mutation known as EGFR T790M dramatically raises the risk of developing lung cancer, even among individuals who have never smoked a single cigarette in their lives (Epidermal Growth Factor Receptor). While somatic changes in lung tissue frequently stem from environmental damage, germline variants are passed directly down through biological families [1]. In a massive collaborative investigation published in Science, researchers demonstrated that nonsmoking carriers face odds more than 60 times higher than unexposed peers [3].
Measuring a Rare Genetic Mutation
Clinical oncologists first detected this inherited anomaly in 2005, identifying the EGFR T790M mutation within a European family that suffered multiple cases of pulmonary malignancy [3]. The Epidermal Growth Factor Receptor gene orchestrates fundamental biological instructions governing cellular growth, division, and survival (a primary receptor tyrosine kinase pathway). When mutations disrupt this pathway, normal regulatory mechanisms falter and cells proliferate uncontrollably into malignant tumors [2]. For years, medical experts recognized that certain lineages carried an exceptionally elevated risk, yet verifying that hazard proved mathematically impossible due to the variant’s scarcity across the broader human population [3].
Progress stalled without large cohorts. Individual clinical practices rarely encountered multiple carriers, leaving the exact biological danger unmeasured for nearly two decades [3].
Solving the measurement bottleneck required pairing clinical oncology with population-scale genomics. Investigators at Dana-Farber Cancer Institute united with geneticists at the 23andMe Research Institute to interrogate inherited vulnerability across millions of individuals [3]. While therapeutic efforts in other medical disciplines focus on reactivating fetal hemoglobin genes to treat inherited blood disorders, this oncology team aimed to isolate inherited DNA variants that initiate pulmonary carcinogenesis [1]. By bridging academic oncology and commercial genotyping databases, the study established the statistical power necessary to evaluate carriers systematically [3].
Scale of the Multimillion-Person Cohort
Evaluating the health trajectories of millions of individuals allowed researchers to overcome the statistical barriers that had previously hindered rare disease research. Dr. Jaclyn LoPiccolo, an attending physician and thoracic oncologist at Dana-Farber Cancer Institute, co-led the extensive effort alongside co-senior author Dr. Pasi A. Jänne and quantitative geneticist Dr. Alexander Gusev. The team evaluated de-identified records from 3.3 million research-consented participants who completed at-home genotyping kits, drawn from an overarching 23andMe cohort of 10 million individuals [2, 3]. Public repositories simply lacked comparable statistical depth; the United States All of Us research program contained only 19 carriers, while the UK Biobank included merely two individuals with the variant [2].
Scale transformed an elusive anomaly into measurable epidemiology. Within the curated 23andMe cohort, investigators identified 641 participants carrying the rare genetic mutation [2]. “Finding a variant this rare, measuring what it does and tracing where it came from are three different scientific challenges,” explained Dr. Joyce Tung, vice president of research at 23andMe Research Institute [3]. That substantial carrier cohort finally provided enough statistical power to calculate reliable odds ratios [2].
Additional verification came from prospective clinical registries. Co-senior authors LoPiccolo and Jänne integrated clinical observations from the INHERIT Study (NCT05587439), conducted in formal partnership with GO2 for Lung Cancer and the Addario Lung Cancer Medical Institute. This clinical trial specifically evaluates germline risk profiles in patients presenting with personal or family histories of thoracic malignancies [3].
Dramatically Elevated Risk Among Nonsmokers
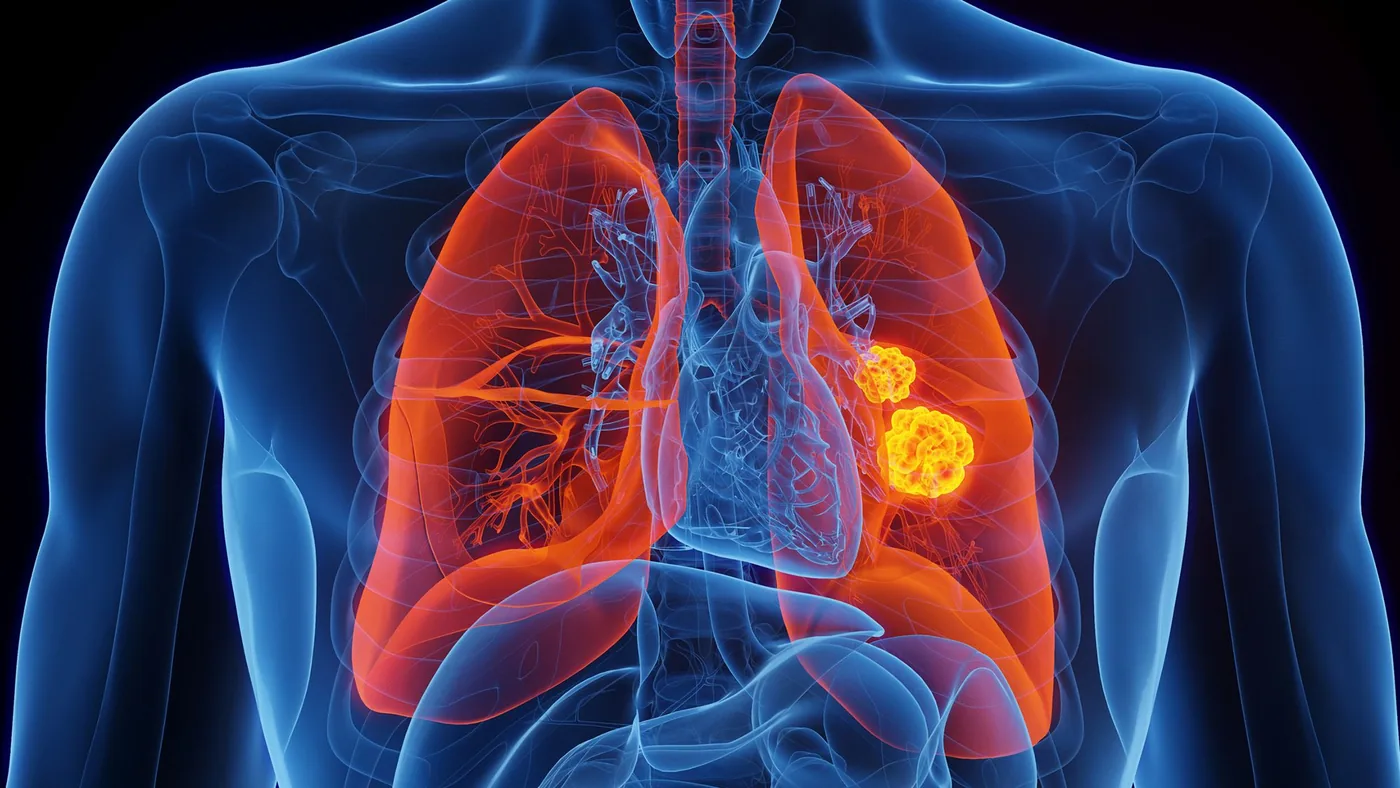
Statistical calculations revealed an astonishing effect size. Across the entire study population, carriers of the variant exhibited 25 times the odds of developing lung cancer compared with non-carriers. The most dramatic finding emerged when analyzing lifelong nonsmokers. Individuals who had never smoked but carried the T790M alteration were 62 times more likely to develop lung cancer than nonsmokers lacking the alteration [2]. That magnitude establishes the mutation as one of the most potent inherited cancer-predisposing variants identified in modern genetics [3].
The heightened risk from the variant eclipses standard behavioral hazards. Cigarette smokers without the mutation faced approximately four times the lung cancer risk of nonsmokers, meaning the inherited alteration alone confers far greater relative hazard than tobacco usage. When genetic susceptibility and environmental toxins collided, the biological damage escalated dramatically. Mutation carriers who smoked suffered an 11-fold increase in cancer odds compared with other smokers [2].
Does this genetic vulnerability extend to other organs? Extensive screening across 17 other common cancers confirmed that the alteration’s lethal impact remains strictly confined to pulmonary tissue. “Smoking is bad for lung cancer. This mutation is bad for lung cancer,” noted Dr. Alexander Gusev of Dana-Farber Cancer Institute. “When you do both, your risk is the sum of those two risks. So, you definitely don’t want to smoke.” [3]. The mutation showed zero statistical association with benign respiratory conditions or extrapulmonary tumors [2].


Appalachian Isolation and Founder Bottlenecks
Geographic mapping uncovered a striking concentration of mutation carriers in the southeastern United States. Across the general population of European ancestry, this rare genetic mutation occurs in approximately 1 out of every 15,850 individuals (about 1 in 15,000). Among participants born in Alabama, Mississippi, and Tennessee, prevalence surged to 1 in 2,078 individuals, reaching 1 in 2,000 in certain localized districts [2, 3]. Historical genealogical records enabled investigators to trace this distinct demographic pattern back across several centuries [2].
Colonial migration patterns catalyzed this regional enrichment. Immigrants from the British Isles carried the rare ancestral variant across the Atlantic Ocean during the early 1700s [2]. Subsequent generations settled within the rugged valleys of Southern Appalachia (an area marked by historical geographic isolation). This physical seclusion generated a powerful founder event and genetic bottleneck, causing the variant to recur across generations rather than dissipate into a wider gene pool [3].
Regional environmental factors compound this inherited genetic vulnerability. Dr. Stephen Chanock, director of the Division of Cancer Epidemiology and Genetics at the National Cancer Institute, noted that geographic clustering helps explain persistent regional lung cancer clusters. Approximately 20% of adults in Appalachia smoke cigarettes, compared with 16% nationwide. Just as modern researchers investigate how inherited genetic mutations influence longevity, epidemiological analyses demonstrate how historical ancestry and regional habits intersect to amplify disease burden [1, 2].
Rethinking Lung Cancer Screening Criteria
Current diagnostic standards remain poorly equipped to detect nonsmoking carriers early. Today, preventive lung screening with low-dose computed tomography (a specialized low-dose CT scan) depends almost exclusively upon documented smoking history. Because nonsmokers rarely qualify for preventative chest scans under existing guidelines, carriers frequently receive diagnoses only after tumors have advanced into late, incurable stages. “Our findings raise the possibility that, in the future, screening could also be dictated by inherited genetic risk,” stated lead author Dr. Jaclyn LoPiccolo [3].
Carrier tumors develop at significantly younger ages than conventional lung cancers. The study revealed that carriers of this rare genetic mutation developed malignancies approximately five years earlier than non-carrier patients on average. Chris Amos, a genetic epidemiologist at Baylor College of Medicine, emphasized that this earlier onset demands immediate adjustments to clinical screening ages irrespective of patient smoking history [2]. Detecting these lesions when they remain localized offers the greatest opportunity for curative surgical intervention before metastatic spread occurs [3].
Carrying the variant also alters clinical pharmacology. Amos observed that knowing a patient’s germline T790M status provides critical guidance for oncologists selecting targeted molecular therapies, as the mutation alters cellular sensitivity to standard EGFR inhibitors [2]. Personalized screening protocols could soon match patients to precise therapeutic regimens long before aggressive tumors emerge [3].
Future Clinical Trials and Counseling
Translating genomic discoveries into active patient protection requires structured clinical trials. Investigators at Dana-Farber Cancer Institute are actively recruiting participants for the prospective INHERIT Study to establish clear radiological screening guidelines for mutation carriers. Simultaneously, the Susan Wojcicki Foundation is supporting participant recruitment for the Lung Cancer Genetics Study in partnership with 23andMe [3]. These initiatives examine how secondary genetic alterations and airborne particulate-matter pollution interact with germline vulnerability to trigger tumor formation [2].
Medical organizations advocate proactive genetic evaluation for individuals with specific ancestral or familial indicators. David Benson, chief executive officer of GO2 for Lung Cancer, stressed that identifying inherited risk empowers families to make informed diagnostic choices. Authors strongly advise genetic counseling for individuals who have multiple relatives diagnosed with thoracic cancer, patients presenting with multifocal lung nodules, or those with ancestral lineages tracing back to the southeastern United States. A genetic counselor can determine whether clinical testing and targeted surveillance are warranted [3].
Will ongoing genomic surveys reveal related oncogenic mutations in unstudied populations? Both Amos and Chanock predict that future sequencing will uncover other variants within the EGFR gene and related metabolic networks [2]. Understanding how this rare genetic mutation operates across diverse ancestral populations provides an indispensable roadmap for precision medicine [1]. Expanding genomic screening will help oncologists catalog inherited thoracic risks systematically [3]. Identifying high-risk individuals before malignant transformation occurs represents the most promising frontier in preventative oncology [1].
- ACADEMIC JOURNAL LoPiccolo, J., Micheletti, S., Shi, J., Wang, W., Saini, S., Lin, K., Xu, W., Fontanillas, P., 23andMe Research Team, Koeller, D. R., Yatzus, H., Williamson, V. G., Avila, J. A., Liautaud, R. B., Fields, N. D., Harper, A., Kotait, V., Izzo, E., Ciupek, A., … Granka, J. M. (2026). Germline EGFR T790M mutation and lung cancer risk. Science, 393(6817). [Article Link]
- ONLINE NEWS Brincat, C. (2026, September 17). Scientists identify rare genetic mutation that dramatically raises risk of lung cancer in nonsmokers. Live Science. [Article Link]
- ONLINE NEWS Dana-Farber Cancer Institute. (2026, September 17). Rare inherited EGFR mutation linked to dramatically increased lung cancer risk. Medical Xpress. [Article Link]
APA 7: TWs Editor. (2026, September 18). Scientists Link Rare Genetic Mutation to Severe Lung Cancer Risk. PerEXP Teamworks. https://perexpteamworks.com/en/rare-genetic-mutation-lung-cancer-risk/


