





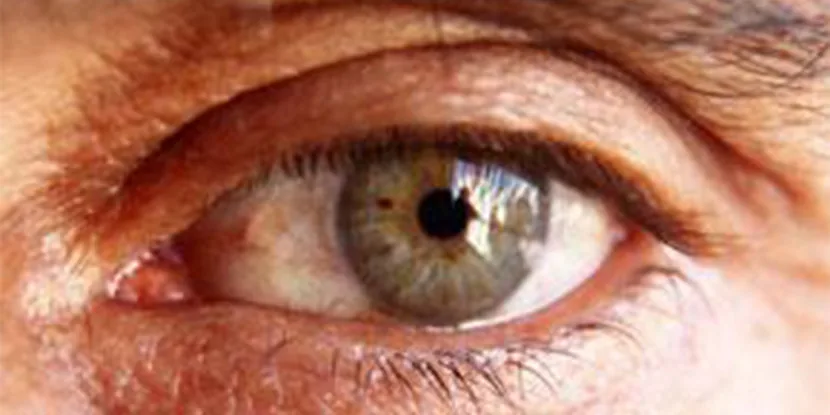
Bell’s palsy is an acute nerve disorder that causes muscles on one side of the face to droop or freeze without warning. The problem occurs when the seventh cranial nerve swells inside the skull [1]. Annual records from the National Institute of Neurological Disorders and Stroke show that between 15 and 30 people per 100,000 get this illness each year [3]. Most patients start to regain muscle control within three weeks [2].
Origins of Bell’s Palsy
Medical history links this illness to Scottish surgeon Sir Charles Bell, who published landmark clinical papers in Edinburgh in 1821 explaining how injury to the seventh cranial nerve halts facial muscle action [4, 5]. Medical doctors classify the illness as an acute lower motor neuron problem of unknown initial origin [6]. It stands as the leading cause of one-sided facial drooping across the globe, accounting for 60% to 75% of acute cases [3]. Onset is swift. A person can lose facial control within hours [1]. Clinical registries show peak rates in adults aged 15 to 45 years [2, 3]. Men and women contract the illness at similar rates in clinics across the world [8].
Data from WebMD and the Centers for Disease Control and Prevention show that about 40,000 people in the United States develop Bell’s palsy annually [8]. An average person faces a lifetime risk of 1 in 60 (about 1.5%) [1, 5]. Risk climbs in adults over age 65, while kids under age 10 rarely get it. Right-sided weakness occurs in 63% of cases [3].
Certain health states raise the risk of facial weakness. Expectant mothers face a risk roughly 3.3 times higher than non-pregnant women, with cases clustering in the third trimester [3, 8]. Patients diagnosed with diabetes also show heightened risk. A nationwide study from the Korean National Health Insurance Service by Dr. H. W. Seo confirmed that diabetic patients face higher incidence and slower recovery [3].

Anatomy of the Temporal Canal
To see why this nerve is so prone to injury, clinicians track the long bony route of cranial nerve VII as it journeys from the brainstem to the face. Nerve fibers exit the brainstem and enter the petrous temporal bone through the internal acoustic meatus. Inside this solid bone, the nerve threads through a narrow, curved hallway named the Fallopian canal, which measures about thirty millimeters in length [4, 9]. Inside this tight tunnel, the nerve swells to form the geniculate ganglion, where sensory fibers for taste part ways from motor branches that steer facial muscles, tears, and saliva [4, 10]. Because bone cannot expand, even small tissue swelling pinches nerve fibers against rock-hard walls [7].
After leaving the geniculate ganglion, the motor trunk drops down and exits the skull base at the stylomastoid foramen [4, 11]. The main trunk then enters the parotid gland before splitting into five terminal motor branches [11]. These branches govern brow movement, eyelid blinking, and mouth posture [1]. Without nerve impulses from the brainstem, facial muscles quickly lose tone and go limp [6].
The dense walls of the temporal bone leave zero room for nerve swelling. When an immune reaction triggers swelling along the nerve sheath, pressure builds fast inside the bony tunnel [7, 10]. This mechanical pinch chokes small blood vessels, starving axons of oxygen and halting nerve traffic [7]. Signals stop. Facial muscles on that side can no longer move [6].
Why the Facial Nerve Swells
Doctors still call this disorder idiopathic because no single trigger explains every case, yet laboratory research points straight to dormant viruses hiding in cranial nerve ganglia [7, 10]. Virologists explain that herpes simplex virus type 1 (HSV-1), the common bug behind oral cold sores, travels up nerve paths during early life and sleeps quietly inside the geniculate ganglion. When emotional stress, poor sleep, or seasonal sickness weakens immune defenses, this dormant virus wakes up and multiplies along nerve fibers [7, 11]. In an influential clinical study of 176 facial palsy cases reviewed in medical literature, laboratory tests found HSV-1 in 31 patients (18%) and varicella zoster virus in 45 patients (26%) [5].
Viral growth prompts an immune attack that harms Schwann cells surrounding nerve fibers [11]. Immune cells release chemical messengers called cytokines, stripping away myelin coats and causing fluid buildup inside the tight bone canal. This immune reaction explains why a patient suffers nerve block even when viral counts in blood stay low. The nerve swells and chokes itself [7].
Medical reports also link acute nerve swelling to mumps, rubella, cytomegalovirus, and colds [2, 8]. Safety surveillance during large immunization drives, including mRNA reviews during Moderna clinical trials, evaluated whether immune triggers raised facial neuropathy rates. A 54-page staff report from the U.S. Food and Drug Administration (FDA) noted four cases in Moderna trials and four in Pfizer trials. Advisory committee members Dr. Paul Offit and Dr. Peter Marks stated that case counts matched normal background rates in the general public [15].
Early Warning Signs
Facial weakness often appears with startling speed, with symptoms starting abruptly and reaching their worst point within 48 to 72 hours [1, 8]. Many people wake up in the morning and notice half of their face feels numb or stiff when trying to wash or smile in the mirror [8, 9]. A mild pain or dull ache behind the ear or in the mastoid bone often shows up a day or two before muscle weakness begins [1, 4]. Once inflammation clamps down inside the bone canal, muscle strength drops fast, leaving the cheek flat and making normal expressions impossible [1, 2].
Loss of muscle power creates clear facial drooping [6]. The eye on the sick side cannot close all the way, leaving a visible gap [1, 4]. Food gets stuck between the cheek and teeth because cheek muscles can no longer push. Drinks leak out from the corner of the mouth. Lip weakness also slurs words during talk [2].
Sensory and gland symptoms often pair with muscle weakness because cranial nerve VII carries mixed nerve fibers [4]. Many patients notice dull or lost taste across the front two-thirds of the tongue, where sensory fibers of the chorda tympani branch travel [2, 10]. Patients may also develop hyperacusis, where everyday sounds seem painfully loud because paralysis of the stapedius muscle stops the middle ear from dampening sound waves [4, 10]. Dry eyes and dry mouth also occur [2].



Differences from a Stroke
How do clinicians tell whether acute facial weakness comes from a stroke or a facial nerve problem? The answer lies in the wiring of upper versus lower motor neuron pathways. A stroke is an upper motor neuron (UMN) problem inside the brain, while Bell’s palsy is a lower motor neuron problem in the cranial nerve. Because the motor cortex in each brain hemisphere sends signals to both sides of the forehead, a person having a stroke can still raise their eyebrows, wrinkle their brow, and shut both eyes tight [4, 10]. A peripheral nerve injury, by contrast, knocks out the whole side of the face [4].
Total half-face weakness confirms a peripheral nerve injury [4]. When asked to look up and frown, a patient cannot move the brow on the sick side [1]. A stroke also brings bodily signs like arm weakness, leg numbness, stumbling, confusion, and slurred speech from brain language centers [8, 10]. Bell’s palsy never weakens arms or legs. Mind and body stay strong [8].
Clinicians also check for other nerve issues, such as myasthenia gravis, which weakens signal handoffs from nerves to muscles. In wooded areas of Wisconsin, Minnesota, and New England, Lyme disease from tick bites causes roughly 25% of facial palsy cases and often strikes both sides [4, 5]. Ramsay Hunt syndrome from chickenpox virus causes severe ear pain and ear blisters, though cases without a rash (called zoster sine herpete) mimic Bell’s palsy closely [4].
Diagnostic Tests in Clinical Care
Guidelines from the American Academy of Otolaryngology–Head and Neck Surgery stress that Bell’s palsy is a clinical diagnosis of exclusion, reached without needing scans or blood draws in standard cases [6, 7]. A doctor checks all cranial nerves by asking the patient to raise eyebrows, close eyes against gentle force, smile wide, and puff cheeks [4]. If facial weakness hits upper and lower muscles equally, with no arm weakness, confusion, or blisters, doctors can confirm the diagnosis right away and start care [6, 7]. Diagnostic accuracy remains very high when relying on this thorough physical exam alone [1].
Doctors score the extent of facial weakness using the House-Brackmann scale, created by Dr. John W. House and Dr. Derald E. Brackmann [4, 5]. This scale runs from grade 1 (normal facial motion) up to grade 6 (total paralysis with no movement) [4]. Doctors use these numbers to track how well a patient recovers over time. It guides treatment choices [6].
When symptoms look unusual or fail to get better after weeks, doctors order deeper testing [1, 6]. Magnetic resonance imaging (MRI) or CT scans can rule out bone fractures, acoustic neuromas, and parotid gland tumors [4, 11]. Electromyography measures muscle electrical signals, and nerve conduction tests clock the speed of electrical pulses along nerve fibers. These tests show whether axons stay alive or suffer deeper harm [2, 11].
Medical Treatment for Bell’s Palsy
Strong evidence from the American Academy of Neurology (AAN) practice guidelines shows that early oral corticosteroids (such as prednisone) are the single best medicine for restoring facial movement [6, 12]. Guidelines advise starting steroid pills within 72 hours of first symptoms to gain maximum benefit [4, 6]. A standard adult course gives 60 milligrams of prednisolone daily for five days, followed by a daily ten-milligram drop over the next five days [4]. A landmark Cochrane review by Dr. V. B. Madhok showed that steroids curb nerve swelling inside the tight bone canal, helping more patients achieve full recovery [13, 14].
Adding antiviral drugs like Valtrex (valacyclovir) or Zovirax (acyclovir) remains controversial [6, 12]. Cochrane systematic reviews show that antivirals add little benefit when combined with steroids in mild or moderate cases [12, 13]. Yet many specialists still prescribe them with steroids in cases of complete paralysis [6, 8]. The goal is fighting active viral growth [6].

Shielding the open eye is an urgent medical priority [1, 4]. Because eyelid muscles fail to shut, the eye dries out, risking exposure keratitis and corneal ulcers. Clinical guidance from the American Academy of Ophthalmology urges using artificial tears often during daytime hours and placing thick eye ointment inside lids before sleep [2, 9]. Taping the eyelid closed with gentle paper tape at night keeps dust out and protects the clear cornea [9].
Recovery in Idiopathic Facial Paralysis
The outlook for Bell’s palsy is bright for most patients, with roughly 70% to 90% regaining normal facial muscle function within three to six months [1, 3]. Early signs of healing usually appear within two to three weeks, starting with subtle gains in cheek tone [1, 9]. Patients who show early recovery within this three-week window almost always make a full recovery. However, adults over age 60 and people with complete initial paralysis face longer healing times [1, 3]. Palsy returns in about 4% to 14% of patients, sometimes on the other side of the face [3].
About 5% to 15% of patients suffer lasting deficits due to flawed nerve regrowth [1, 3]. As growing axons search for muscle targets, they can hook up to the wrong muscle fibers, causing synkinesis [3, 9]. This mixed wiring creates accidental twitches, like an eye blinking whenever a person smiles. Misguided nerve fibers can also trigger tear flow during meals, a condition known as crocodile tears or epiphora [3, 10].
When healing stalls, physical therapy can help retrain muscle control and stop permanent muscle tightening [8, 9]. Botulinum toxin shots help relax overactive or misfiring muscle bundles, restoring facial symmetry [4, 6]. When severe weakness lasts past one year, surgeons can perform nerve transfers or muscle sling procedures to restore facial balance and help lids shut firmly [1, 11]. Most patients recover well without surgery [1].
- WEBSITE Cleveland Clinic. (2023, September 6). Bell’s Palsy. Cleveland Clinic Health Library. [Article Link]
- WEBSITE MedlinePlus. (2026, April 5). Bell palsy: MedlinePlus Medical Encyclopedia. U.S. National Library of Medicine. [Article Link]
- WEBSITE Medscape. (2026, October 12). Bell Palsy: Background, Epidemiology, Etiology. Medscape Reference. [Article Link]
- WEBSITE Vincent, P., & Tidy, C. (2024, August 12). Facial nerve palsy. Patient.info. [Article Link]
- WEBSITE Wikipedia contributors. (2026). Bell’s palsy. Wikipedia, The Free Encyclopedia. [Article Link]
- ACADEMIC JOURNAL Baugh, R. F., Basura, G. J., Ishii, L. E., Schwartz, S. R., Drumheller, C. M., Burkholder, R., Deckard, N. A., Dawson, C., Driscoll, C., Gillespie, M. B., Gurgel, R. K., Halperin, J., Khalid, A. N., Kumar, K. A., Micco, A., Munsell, D., Rosenbaum, S., & Vaughan, W. (2013). Clinical Practice Guideline: Bell’s Palsy. Otolaryngology–Head and Neck Surgery, 149(S3). [Article Link]
- ACADEMIC JOURNAL Zhang, W., Xu, L., Luo, T., Wu, F., Zhao, B., & Li, X. (2020). The etiology of Bell’s palsy: a review. Journal of Neurology, 267(7), 1896-1905. [Article Link]
- WEBSITE Walker-Journey, J., & WebMD Editorial Team. (2023, November 14). What Is Bell’s Palsy? WebMD. [Article Link]
- WEBSITE Kahn, A., & Larson, J. (2017, August 29). Bell’s Palsy: Causes, Symptoms, Diagnosis, Treatment, Outlook. Healthline. [Article Link]
- WEBSITE Rubin, M. (2025, August 1). Bell Palsy – Brain, Spinal Cord, and Nerve Disorders. Merck Manual Consumer Version. [Article Link]
- WEBSITE Taylor, D. C. (2022, September 19). Bell’s Palsy (Facial Nerve Problems) Symptoms, Treatment, Causes. MedicineNet. [Article Link]
- ACADEMIC JOURNAL Gronseth, G. S., & Paduga, R. (2012). Evidence-based guideline update: Steroids and antivirals for Bell palsy. Neurology, 79(22), 2209-2213. [Article Link]
- ACADEMIC JOURNAL Madhok, V. B., Gágyor, I., Daly, F., Somasundara, D., Sullivan, M. K., Gammie, F., & Sullivan, F. (2016). Corticosteroids for Bell’s palsy (idiopathic facial paralysis). Cochrane Database of Systematic Reviews, 2016(7), CD001942. [Article Link]
- ACADEMIC JOURNAL Somasundara, D., & Sullivan, F. (2016). Management of Bell’s palsy. Australian Prescriber, 40(3), 94-96. [Article Link]
- ONLINE NEWS Higgins-Dunn, N. (2020, December 15). FDA staff recommends watching for Bell’s palsy in Moderna and Pfizer vaccine recipients. CNBC. [Article Link]


