






Insulin resistance describes a metabolic state where cells in skeletal muscle, fat tissue, and the liver fail to respond normally to the hormone insulin. Beta cells in the pancreas produce insulin after meals to move glucose out of the blood and into tissues for energy storage. When target cells become blunt to this hormonal signal, the pancreas compensates by secreting higher amounts of insulin to clear sugar from circulation. Why does this cellular communication break down over time? Chronic nutrient overload, inherited risks, and low-grade tissue inflammation gradually impair receptor signaling pathways. When beta cells can no longer produce enough hormone to overcome peripheral resistance, blood sugar climbs, setting off prediabetes and long-term metabolic strain [1].
How Cells Process Blood Glucose
Under healthy conditions, blood sugar management relies on a tightly controlled feedback loop between the pancreas and peripheral tissues. Endocrine beta cells clustered in the islets of Langerhans monitor circulating glucose and release insulin into the bloodstream as concentrations climb following meals. In skeletal muscle and fat tissue, circulating insulin binds to the alpha subunit of the insulin receptor on the cell surface, turning on the tyrosine kinase activity of the intracellular beta subunit. This biochemical trigger mobilizes glucose transporter type 4, known as GLUT4, from storage vesicles inside the cell to the outer cell membrane, letting glucose enter through facilitated diffusion so tissues can use it for immediate work or long-term energy storage [4].
The liver responds differently because it regulates sugar production rather than simply taking in fuel for storage. When insulin levels rise after eating, healthy liver cells quickly turn off gluconeogenesis and stop breaking down stored glycogen into circulating sugar. This process contrasts with the autoimmune destruction seen in type 1 diabetes, where pancreatic beta cells die and produce no insulin at all.
When cells lose their sensitivity to circulating insulin, normal hormone levels can’t suppress hepatic sugar release or open muscle transport gates. Skeletal muscle accounts for about 80 percent of post-meal glucose uptake, making it the main site of peripheral impairment. As muscle cells fail to absorb sugar, blood glucose stays high. In response, the pancreas pumps out more insulin, causing chronic hyperinsulinemia that strains beta cells and alters systemic lipid handling [6].
Why Insulin Resistance Develops in Tissue
Clinical research shows that peripheral tissue blunting often starts in skeletal muscle before spreading elsewhere in the body. In a clinical trial published in Gastroenterology, Dr. Kerry Lee Milner and Professor Don Chisholm from the Garvan Institute of Medical Research in Sydney, working with Professor Jacob George from the Storr Liver Unit at Westmead Hospital, studied 29 patients with chronic hepatitis C. Scientists have known that hepatitis C makes people three to four times more likely to get type 2 diabetes. Surprisingly, the researchers found that insulin resistance was confined almost entirely to muscle tissue, with little to no resistance detected in the liver, even though hepatitis C is fundamentally a liver infection [2].
The trial produced an even more unexpected finding about liver fat. Fifteen participants had high levels of liver fat, yet they had the exact same degree of muscle insulin resistance as the fourteen participants without fatty livers. Professor Chisholm said that while many scientists view liver fat as the main driver of resistance, this study proves that muscle defects can arise independently [2].
Inside muscle fibers, excess fat buildup disrupts normal biochemical signaling cascades. Intramyocellular lipids generate toxic breakdown products like diacylglycerol, which block insulin receptor substrate phosphorylation. This interruption stops downstream signals from moving GLUT4 transport vesicles to the cell surface. Glucose stays stuck in the bloodstream while muscle cells starve for glycogen fuel, worsening blood sugar spikes and forcing the pancreas to release higher amounts of insulin to maintain metabolic balance [6].
Endoplasmic Reticulum Stress in the Liver
While muscle tissue handles glucose disposal, the liver controls baseline sugar release through gluconeogenesis. Researchers at the Salk Institute for Biological Studies uncovered how cellular stress disrupts this hepatic control. In a study published in Nature, a research team led by Professor Marc Montminy in the Clayton Foundation Laboratories for Peptide Biology, working with first author Yiguo Wang, Ph.D., research technician Liliana Vera, and mass spectrometry director Wolfgang H. Fischer, Ph.D., showed how high-fat diets trigger stress in the endoplasmic reticulum of liver cells. The endoplasmic reticulum serves as the protein factory inside cells, and persistent nutrient excess disrupts its delicate folding duties, setting off a chronic stress cascade that alters liver metabolism [3].
Under healthy conditions, a regulatory protein called CRTC2 stays outside the cell nucleus during fed states. When fasting begins, CRTC2 slips inside the nucleus, pairs with CREB, and turns on genes needed to make glucose. Under brief stress, CRTC2 instead binds to a survival factor called ATF6a, which shuts down glucose production to help stressed cells recover and save energy [3].
Persistent obesity breaks this safety mechanism. Chronic stress depletes ATF6a over time, leaving CRTC2 free to join CREB without opposition. As a result, the molecular switch gets stuck in the on position. The liver keeps churning out glucose day and night, even when blood sugar is already high. Montminy said this rogue pathway explains why sugar production fails to shut down, driving high fasting glucose in both obese people and lean individuals under metabolic stress [3].
Physical Markers and Warning Signs
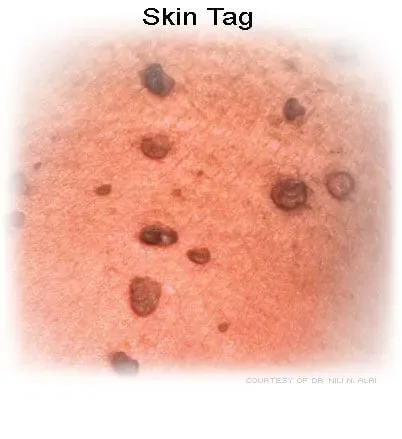
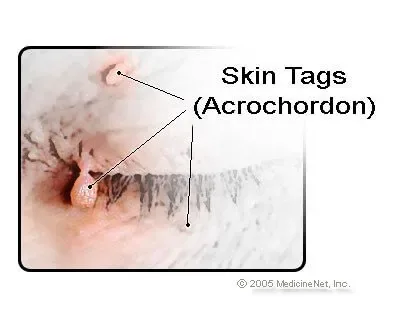
Early metabolic dysfunction rarely causes pain or obvious illness, but specific skin changes give useful clues about what is happening inside. The clearest skin sign is acanthosis nigricans, where skin darkens and thickens into velvety patches within body folds like the back of the neck, armpits, and groin. High levels of circulating insulin bind to insulin-like growth factor 1 receptors on skin cells, causing them to multiply faster than normal. People with resistance also often develop skin tags, small soft growths that hang from the eyelids, neck, and upper chest. When clinicians identify these harmless skin growths during routine health checks, they know to evaluate the patient for underlying metabolic strain and impaired glucose handling [4].
Body measurements and patient backgrounds provide clear ways to gauge risk. A waistline over 40 inches in men or 35 inches in women points to deep belly fat, which closely tracks with reduced insulin sensitivity. Goutham Rao, writing in American Family Physician, reported that a waist-hip ratio exceeding 1.0 for male individuals or 0.8 for female individuals signals central fat deposition [5]. In addition, federal data show heightened vulnerability among African American, American Indian, Asian American, and Latino communities [1].
Internal organs also show signs of metabolic disruption across several clinical conditions. Polycystic ovary syndrome, commonly called PCOS, brings irregular periods and excess testosterone in women driven by high insulin stimulating ovarian tissue. Faulty hepatic lipid storage triggers nonalcoholic fatty liver disease, designated NAFLD, which can progress to cirrhosis if unmanaged [4]. Secondary resistance also surfaces in endocrine disorders like Cushing syndrome and among patients receiving antiretroviral therapy for HIV [1].
Diagnostic Tests for Insulin Resistance
Doctors identify metabolic changes by checking how well the body clears glucose from the blood. The National Institute of Diabetes and Digestive and Kidney Diseases lists three common blood tests used to detect prediabetes. A fasting plasma glucose test checks blood sugar after an overnight fast, where readings between 100 and 125 milligrams per deciliter indicate prediabetes. The hemoglobin A1C test measures average blood sugar over the past three months, with scores between 5.7 percent and 6.4 percent marking the prediabetic range. A two-hour oral glucose tolerance test checks blood sugar after drinking a sweet 75-gram liquid, where readings between 140 and 199 milligrams per deciliter indicate impaired tolerance [1].
Specialized lipid panels offer another window into metabolic health. The Lipoprotein Insulin Resistance Index uses nuclear magnetic resonance spectroscopy to evaluate six blood lipid markers, including large very-low-density lipoproteins and small low-density lipoproteins. The test gives a score from 0 to 100. Scores under 50 mean low resistance, 50 to 80 show intermediate risk, and scores above 80 indicate high insulin resistance [8].
Population research confirms that metabolic markers shift long before fasting sugar climbs into diabetic territory. In a study published in BMC Medicine, Q. Wang and colleagues evaluated 5,340 Finnish individuals, tracking circulating metabolic profiles during oral glucose tolerance tests. The team identified clear shifts in amino acids and lipid particle sizes across a discovery cohort of 4,745 adults and a replication group of 595 seniors, showing that cellular resistance alters whole-body metabolism well before blood glucose reaches diagnostic thresholds [9].

Progression to Type 2 Diabetes
Moving from healthy insulin sensitivity to overt diabetes happens gradually as pancreatic compensation breaks down. In 2021, about 97.6 million adults aged 18 and older in the United States had prediabetes, according to the NIDDK. For years or even decades, high insulin output keeps blood sugar within normal lab limits by forcing stubborn cells to absorb glucose. But pancreatic beta cells eventually wear out from constant overproduction. When the pancreas can’t make enough insulin to meet the body’s heavy demands, blood sugar begins to rise. People with prediabetes face a strong chance of developing type 2 diabetes within five to ten years if they make no lifestyle adjustments to protect beta-cell function [1].
Blood vessel complications also climb as glucose regulation slips. In a study published in the Journal of the American Heart Association, N. Sasaki and fellow researchers tracked atomic bomb survivor health checkup examinees between 1982 and 2017. High blood pressure was found in 36.3 percent of people with normal glucose tolerance, jumping to 50.1 percent in those with impaired fasting glucose and reaching 63.8 percent in people with diabetes [10].
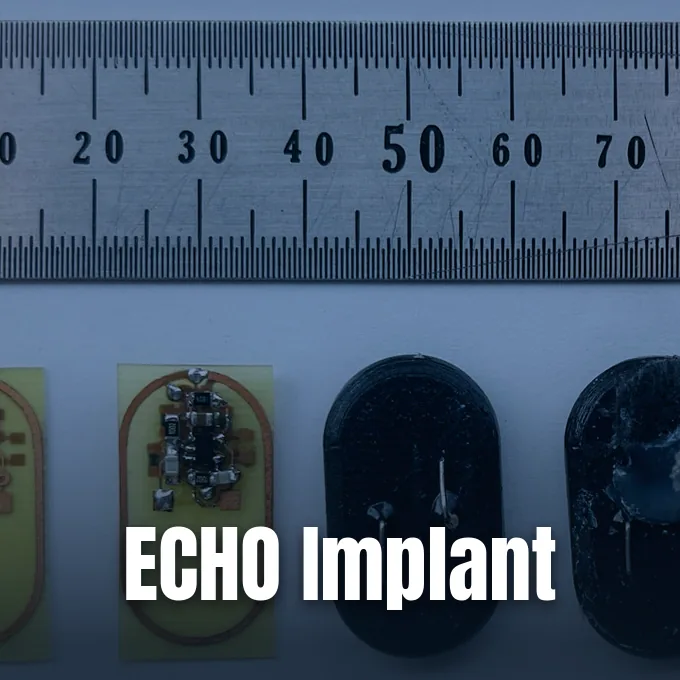
Protecting heart health means tackling metabolic resistance early. In the IRIS clinical trial published in the New England Journal of Medicine, W. N. Kernan and colleagues followed 3,876 nondiabetic patients who had a recent stroke or transient ischemic attack along with insulin resistance. Giving patients pioglitazone cut stroke and heart attack rates from 11.8 percent to 9.0 percent over 4.8 years, while cutting new diabetes cases from 7.7 percent to 3.8 percent [11]. On the technology front, scientists are testing an electrocatalytic implant that regulates blood sugar to offer alternative ways to control glucose levels.
Why Does Insulin Resistance Affect Weight?
Why does weight loss feel so hard once cells stop listening to insulin? The answer comes down to how insulin directs energy storage. Insulin acts as a storage signal that tells fat cells to lock up calories as triglycerides while stopping them from breaking fat down for fuel. While muscle cells ignore insulin and stay starved of energy, fat tissue remains responsive to storage cues, trapping calories and triggering hunger and intense sugar cravings. At the same time, expanding belly fat releases inflammatory chemical signals like tumor necrosis factor-alpha and interleukin-6 through the IKK-beta and NF-kappa-B pathway, which travel through the blood and make muscle and liver cells even more resistant [7].
Inherited genetics also explain why some people carry higher metabolic risk. Large genetic scans identify variations near the NAT2, GCKR, and IGF1 genes that blunt insulin action. Scientists estimate that these genetic markers account for 25 to 44 percent of the heritable risk for resistance, showing why some lean people struggle with blood sugar while some heavier people maintain normal insulin sensitivity [7].

Building muscle early in life helps shield the body from future metabolic trouble. In a study published in Epidemiology and Health, S. Jun and co-authors examined 219 young participants from the Ewha Birth and Growth Study. The team tested grip strength relative to body weight at ages 7 to 9 and reassessed blood markers at ages 13 to 15. Kids with higher grip strength had lower fasting insulin and better HOMA-IR scores in their teen years, proving that childhood muscle fitness protects long-term insulin sensitivity [12].
Lifestyle Changes for Metabolic Recovery
Reversing cellular blunting starts with practical habits that help cells respond to insulin again. The Diabetes Prevention Program, funded by the National Institutes of Health, proved that losing 5 to 7 percent of body weight through healthy eating and regular movement cut diabetes risk by 58 percent in high-risk adults. Trimming body weight drains excess fat from liver and muscle cells, clearing toxic lipid byproducts and allowing cell surface receptors to pass signals smoothly into cells once more. In addition, physical exercise activates muscle glucose uptake through alternative routes that don’t depend on insulin, letting working muscles pull sugar straight from the bloodstream during activity [1].
Dietary choices also support metabolic health. Eating plenty of soluble fiber slows down digestion and prevents sharp sugar spikes, which eases the burden on the pancreas. Goutham Rao advises getting at least 30 minutes of moderate activity, such as walking, on most days [5]. Research into a clinical evaluation of time-restricted eating shows that meal timing also helps cells handle energy efficiently.
When lifestyle habits need extra backup, doctors turn to established medications. Metformin is often the first choice, working to dial down glucose output from the liver while helping muscle tissue take in sugar. In a study published in the American Journal of Physiology-Endocrinology and Metabolism, N. Rasouli and colleagues tested pioglitazone at 45 mg daily against metformin at 2,000 mg daily for ten weeks in 23 patients with impaired glucose tolerance. Pioglitazone boosted insulin sensitivity by 65 percent and cut muscle fat by 34 percent, showing that medical therapy can directly reverse lipid accumulation in peripheral tissue [13].
- WEBSITE National Institute of Diabetes and Digestive and Kidney Diseases. (2026, May 5). Insulin Resistance & Prediabetes. [Article Link]
- ONLINE NEWS ScienceDaily. (2010, March 10). Surprising findings about Hepatitis C and insulin resistance. Garvan Institute of Medical Research. [Article Link]
- ONLINE NEWS ScienceDaily. (2009, June 22). How Obesity Increases The Risk For Diabetes. Salk Institute for Biological Studies. [Article Link]
- WEBSITE Stöppler, M. C., & Jacob, D. (2025, September 5). Insulin Resistance Causes, Diabetes, Symptoms, Treatment, Diet. MedicineNet. [Article Link]
- ACADEMIC JOURNAL Rao, G. (2001, March 15). Insulin Resistance Syndrome. American Family Physician, 63(6), 1159-1163. [Article Link]
- WEBSITE Medscape. (2025, March 17). Insulin Resistance: Background, Pathophysiology, Etiology. [Article Link]
- WEBSITE Wikipedia. Insulin resistance. [Article Link]
- WEBSITE Wikipedia. Lipoprotein Insulin Resistance Index. [Article Link]
- ACADEMIC JOURNAL Wang, Q., Jokelainen, J., Auvinen, J., Puukka, K., Keinänen-Kiukaanniemi, S., Järvelin, M., Kettunen, J., Mäkinen, V., & Ala-Korpela, M. (2019). Insulin resistance and systemic metabolic changes in oral glucose tolerance test in 5340 individuals: an interventional study. BMC Medicine, 17(1). [Article Link]
- ACADEMIC JOURNAL Sasaki, N., Ozono, R., Higashi, Y., Maeda, R., & Kihara, Y. (2020). Association of Insulin Resistance, Plasma Glucose Level, and Serum Insulin Level With Hypertension in a Population With Different Stages of Impaired Glucose Metabolism. Journal of the American Heart Association, 9(7). [Article Link]
- ACADEMIC JOURNAL Kernan, W. N., Viscoli, C. M., Furie, K. L., Young, L. H., Inzucchi, S. E., Gorman, M., Guarino, P. D., Lovejoy, A. M., Peduzzi, P. N., Conwit, R., Brass, L. M., Schwartz, G. G., Adams, H. P., Berger, L., Carolei, A., Clark, W., Coull, B., Ford, G. A., Kleindorfer, D.,. Tanne, D. (2016). Pioglitazone after Ischemic Stroke or Transient Ischemic Attack. New England Journal of Medicine, 374(14), 1321-1331. [Article Link]
- ACADEMIC JOURNAL Jun, S., Park, H., Lee, H., Lee, H. A., Hong, Y. S., & Park, H. (2025). Prospective association between handgrip strength in childhood and the metabolic syndrome score and insulin resistance indices in adolescence: an analysis based on the Ewha Birth and Growth Study. Epidemiology and Health, 47, e2025001. [Article Link]
- ACADEMIC JOURNAL Rasouli, N., Raue, U., Miles, L. M., Lu, T., Di Gregorio, G. B., Elbein, S. C., & Kern, P. A. (2005). Pioglitazone improves insulin sensitivity through reduction in muscle lipid and redistribution of lipid into adipose tissue. American Journal of Physiology-Endocrinology and Metabolism, 288(5), E930-E934. [Article Link]


